CUH Logo

Mobile menu open

Diabetes & Pregnancy: type 1 diabetes (managed with injected insulin)

Patient information A-Z

Preparing for pregnancy with type 1 diabetes

This leaflet has been written to give you, your partner, and your family helpful information to prepare for pregnancy with type 1 diabetes. Although having type 1 diabetes means that your pregnancy carries a higher risk, with the right preparation you can reduce this risk and achieve the best pregnancy experience and outcome for you and your baby.

  • There are several things that will help you to be ‘pregnancy ready’ and it is helpful to allow yourself 6-12 months for pre-pregnancy planning.
  • Please continue with effective contraception until you are ‘pregnancy ready’.
  • If your HbA1c is greater than 86mmol/mol it is advised that you avoid pregnancy. This is a national recommendation from the National Institute for Health and Care Excellence (NICE NG3, 2015).
  • Contraception information (opens in a new tab).
  • Family Planning Association (opens in a new tab).
Top 5 tips for getting yourself pregnancy ready

1) Blood glucose levels

  • Aim for an HbA1c as close to 48mmol/mol, or less, as possible without causing problematic hypoglycaemia.
  • Review your glucose levels more frequently; useful times to look are before and after meals and before bed.
  • You are aiming to keep your blood glucose between 3.5 and 10.0mmol/l.
  • Remember, any improvement in glucose levels will reduce risk.

2) Start taking 5mg folic acid daily for at least three months before trying for a pregnancy. Folic acid is a B vitamin that helps support brain and spinal cord development, it takes three months to build levels up, to maximise its full protective effect. This dose is only available on prescription from your GP. This can be taken alongside a ‘routine’ (pre) pregnancy multivitamin that also contains a small amount of folic acid (400mcg).

3) Medication review

  • Insulin is safe for pregnancy.
    If you take other medications such as ACE inhibitors (prescribed for blood pressure and/or kidney protection) or statins (prescribed for high cholesterol), these will need to be stopped or changed to pregnancy safe options.
  • Review of medications prescribed for other medical conditions – choosing the safest options for you and your pregnancy, optimising doses.

4) Healthy weight - there is good evidence showing that being at a healthy weight before becoming pregnant improves the health and outcome of your pregnancy. Being overweight carries independent risks such as high blood pressure, risk for pre-eclampsia, difficulty giving birth and unhealthy weight gain in your baby. If you are overweight, any weight loss prior to your pregnancy will be of benefit.

5) Eye and kidney checks are really important, please ensure that your eye and kidney checks are up to date.

Smoking - if you smoke, it is beneficial for you, your pregnancy, and the health of your unborn baby to stop smoking. Your maternity team will refer you to your local smoking support service. Help can be found at:

Vitamin Supplements
  • The recommendation is to take 5mg folic acid daily for at least 3 months prior to the pregnancy and continue until the end of week 12 once this date is confirmed by your dating scan.
  • All pregnant women are recommended to take vitamin D (10 micrograms) throughout their pregnancy and whilst breastfeeding. This can be taken as a separate supplement or as part of a combined pregnancy specific vitamin and mineral supplement. Vitamin D is essential for healthy bone formation in your baby.
  • If you are vegan, it is recommended that you take an iodine supplement of 150mcg daily.

Already pregnant? – please do not panic, start taking 5mg folic acid daily, if you have not already and contact the pregnancy team (contact details can be found at the end of the leaflet).

Help to stop smoking :

Other useful sources of information include:

Support

We have a team of doctors, nurses, dietitians and midwives experienced in supporting women with diabetes during pregnancy.

We can see you regularly in clinic.

  • Diabetes and Women’s Health Clinic: we can see you every 2-3 months to support you preparing for pregnancy.
  • Antenatal Clinic: once pregnant we can see you as often as required; usually every 2-3 weeks.

Email support (opens in a new tab) with any questions. We encourage you to share your pump/ glucose sensor/ glucometer upload with us to support you with your glucose management.

Emergency out of hours number: 01223 960993.

  • Monday to Friday: 6am-9am and 4pm-11pm.

(9am-4pm – normal service within working hours: 01223 348790).

  • Weekends and Bank Holidays: 6am-11pm.
What to expect in pregnancy

Once pregnant you may notice quite early on that your diabetes and glucose management is different: This is normal.

  • Up to 8 weeks you may notice your glucose running higher and / or being more variable.
  • Between 8-16 weeks you will become more insulin sensitive and will need to take greater care around hypo avoidance – please see section on hypoglycaemia.
  • From 16 weeks you will notice your insulin requirements will start to rise as you become more insulin resistant. Insulin resistance is a normal development as your pregnancy progresses and is caused by pregnancy hormones. Towards the end of your pregnancy, you may be taking 3-4 times the amount of insulin compared to the start of pregnancy. You will also find the balance of insulin changes to needing more with your meals and less background or basal. At around 36 weeks insulin resistance plateaus and a 10% reduction in insulin requirements can be normal.

A key change to glucose levels in pregnancy is that they tend to swing up more after meals, especially after breakfast. Please see diet section for tips on how to minimise this (from page 6 onwards).

  • By 24 weeks of pregnancy, it is recommended that your HbA1c measurement is below 43 mmol/mol. This has been shown to reduce the risk of your baby growing bigger than is healthy for them, needing an admission to neonatal intensive care unit (NICCU) or your baby having a low blood glucose after birth.
Glucose ranges for pregnancy
  • On waking 4.0-5.3mmol/l (please review as soon after waking as possible, ideally within 10 to 15 minutes of waking).
  • 1 hour after meals less than 7.8mmol/l.
  • 2 hours after meals less than 6.4mmol/l.

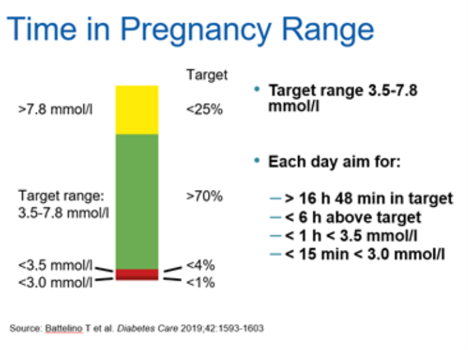
Sensor time in range

  • At least 70% time in range (3.5-7.8mmol/l).
  • Less than 25% above range (greater than 7.8mmol/l).
  • Less than 5% below range (less than 3.5mmol/l).
  • Less than 1% below 3.0mmol/l.
Pregnancy glucose target chart showing more than 70% of time in the 3.5 to 7.8 mmol/L target range, less than 25% above range, less than 4% below 3.5 mmol/L, and less than 1% below 3.0 mmol/L.

You may find you start your pregnancy closer to 50% time in range; we will work closely with you to steadily increase this time and remember every 5% more time spent in range has been shown to reduce risk.

Please see Top Tips information leaflet for using sensors in pregnancy.

Diabetes tech in pregnancy (opens in a new tab) has several educational videos about using diabetes technology in pregnancy.

When working to achieve at least 70% time in range, it will become important to keep the post-meal and overnight glucose in range, as well as the pre-meal and pre-bed.

What you eat and drink will play an important role in your ability to achieve this.

It is also important that you eat a healthy balanced diet; Healthy eating in pregnancy (opens in a new tab) is a useful source of information.

Optimising blood glucose levels at mealtimes

Eating the right type of carbohydrate

  • Carbohydrate foods have a direct impact on your blood glucose, so being careful with the type of carbohydrate eaten will become very important.
  • You may notice carbohydrates that have worked well before no longer work well in pregnancy and you will need to find alternatives.
  • The table below lists those foods that many women find need to be avoided with suitable alternatives.

You may find it helpful to keep a food diary at different stages during your pregnancy to identify carbohydrate types and impact on glucose if out of range. This can help to make better choices.

REFINED CARBOHYDRATES TO AVOID ALTERNATIVES TO REPLACE WITH
REFINED CARBOHYDRATES TO AVOID Bread
All white breads including rolls, pitta, crumpet, croissant, panini, wraps, bagels,pizza
Baguette
Naan / Paratha / chapati / roti (made with white flour)

Bought sandwiches often have higher sugar content
ALTERNATIVES TO REPLACE WITH Bread
Wholewheat, wholegrain, wholemeal varieties of breads
Sourdough bread
Rye bread
Paratha / chapati / roti / puri / thepla if made with wholemeal flour
Freezing bread first lowers impact on glucose
REFINED CARBOHYDRATES TO AVOID Rice / Pasta / Grains / Pulses
Short grain and sticky rice
 
Ground foods such as ground rice / semolina / tapioca / cornmeal / tapioca: idli, fufu, pap, gari, banku, pounded yam
Rice flour noodles: string hoppers
Foods made with ground lentils: dosa, papadum, vada, idli
ALTERNATIVES TO REPLACE WITH Rice / Pasta / Grains / Pulses
Basmati rice (rinse well before cooking)
All pasta
(Cooling rice, pasta and potato after cooking and then eating cold or re-heating fully will lower the impact on glucose)
Bulgar wheat / couscous / quinoa
Peas, beans, lentils
REFINED CARBOHYDRATES TO AVOID Potatoes / root vegetables
Processed potato products:
Oven chips / French fries / smiley faces / waffles / croquettes / frozen roast potatoes / instant potatoes
Roasted parsnip may not work well
Foods made with ground yam / plantain / cassava: gari, eba, pounded yam, amala, banku,
vada
ALTERNATIVES TO REPLACE WITH Potatoes / root vegetables
New and boiled potatoes are best
Homemade wedges / chips / roast potatoes
Small baked potato / mashed potato may be tolerated
Sweet potato / yam / plantain and cassava if boiled, steamed or roast
REFINED CARBOHYDRATES TO AVOID Whiteflour-based foods
Cakes, rusk
Biscuits
Low fibre crackers and crispbreads e.g. cream crackers, water biscuits
Pastry – pies, pasties, quiche, sausage rolls, spring roll, samosa, patties
Yorkshire pudding, dumplings
Breaded and battered foods – fish fingers, battered/breaded fish
ALTERNATIVES TO REPLACE WITH High fibre-based foods
Biscuits: plain wheatmeal digestives, plain hobnobs, Hovis, Nairn oat biscuits (one or two)
High fibre crackers and crispbread: oatcakes, Ryvita
REFINED CARBOHYDRATES TO AVOID Fruit
All melon varieties, pineapple, mango
Dried fruit including dates and prunes
Tinned fruit in syrup
ALTERNATIVES TO REPLACE WITH Fruit
Apple, pear, orange, satsuma (1-2), plums (2), kiwi (2), small banana, grapes (10-12), peach, nectarine
Berry fruits have the lowest impact on glucose: strawberry, raspberry, blueberry, blackberry. Make the most of when in season and buy frozen when not.
Tinned fruit in natural juice – wash away the juice
REFINED CARBOHYDRATES TO AVOID Yogurt and dairy
Chocolate mousse
Chocolate / jam cornered or layered yogurt
Most ice creams
Sorbet
Custard
Condensed, evaporated milk
Kheer
ALTERNATIVES TO REPLACE WITH Yogurt and dairy
Yogurt: natural, Greek, fruit, Skyr or Scandinavian style fromage frais
(Aim for less than 15g total carbohydrate per portion or pot)
Cream and crème fraiche are carbohydrate free
REFINED CARBOHYDRATES TO AVOID Snacks
Sweets
Mints
Chocolate
Processed savoury snacks: Hula Hoops, Skips, Quavers, Pringles, Baked crisps
Puff puff, mandazi, baklava, Shakar Para, barfi, jalebi, Ladoo
ALTERNATIVES TO REPLACE WITH Snacks
4 small squares of 70% cocoa solids chocolate
Sugar free sweets or mints
Natural or salted popcorn
Savoury snacks: sliced potato crisps such as Walkers or kettle
Vegetable crisps
REFINED CARBOHYDRATES TO AVOID Drinks
Fruit juice
Vegetable juice
Smoothies (even if home-made)
Milk shake
Hot chocolate
Full sugar squash and fizzy drinks
Sugar containing flavoured waters
Coffees made with sugary syrups
ALTERNATIVES TO REPLACE WITH Drinks
Water
Sugar free squash and sugar free fizzy drinks
Tea and coffee made with a small amount of milk
Fruit or mint tea
Milky coffees (latte, flat white, cappuccino), glass milk – keep to between meals rather than with meals due to carbohydrate content
Sugar free flavouring syrups can be used
REFINED CARBOHYDRATES TO AVOID Sugar and preserves
Sugar, glucose, maltose, dextrose, treacle, and syrup
Jaggery
Jam & marmalade (including “diabetic” varieties), honey, lemon curd, maple syrup,
chocolate spread
ALTERNATIVES TO REPLACE WITH Sugar and preserves
Artificial sweeteners if a variety are used and in small quantities.
Examples:
Splenda, Sweetex, Hermesetas, Nutrasweet, Canderel, Stevia
Nut butters such as peanut butter (without added sugar)
Marmite, Vegemite
REFINED CARBOHYDRATES TO AVOID Ready meals, packets, jars and take aways
Some ready meals and sauces contain significant amounts of sugar, for example sweet and sour sauces, jar, or packet Chinese sauces
Chinese takeaway, korma
Baked beans, tinned spaghetti
ALTERNATIVES TO REPLACE WITH Ready meals, packets, jars and take aways
It can be helpful to keep some quick meals / foods handy for busy days:
Sachets ready cooked basmati rice, quinoa, lentils
Fresh pasta with sauce
Pasta based ready meals can work well for glucose
Frozen vegetables
Tomato based curries
Reduced sugar baked beans (drain off sauce)
Timing of bolus insulin (mealtime insulin)

When pregnant, the absorption of insulin slows down and so it becomes even more important to give your bolus insulin before eating.

  • In early pregnancy give insulin 15-20 minutes before eating.
  • As your pregnancy progresses this time will need to gradually extend to 30-45 minutes. Think about how you can structure your day to help achieve this.
Eating the right amount of carbohydrate
  • Carbohydrate is an important part of a healthy balanced diet providing you with a useful source of energy for your body and essential vitamins, minerals and fibre.
  • It is important to eat enough carbohydrate to keep your diet nutritionally balanced but not too much to challenge your glucose levels.
  • Women who eat more than 200g carbohydrate per day tend to see more glucose readings out of range. Remember that all carbohydrate converts to glucose.
  • Diets containing less than 120g carbohydrate tend to be more nutritionally inadequate.
  • Glucose levels are more likely to stay in range when carbohydrate is spread over three smaller meals with carbohydrate snacks mid-morning and mid-afternoon.

The amount of carbohydrate that you tolerate is likely to change as your pregnancy progresses and we will review this with you at your clinic appointments.

You may find the carbohydrate amounts below a good place to start.

  • Breakfast: 15-20g carbohydrate
  • Mid-morning snack: 5-15g carbohydrate
  • Lunch: 40-50g carbohydrate
  • Mid-afternoon snack: 5-15g carbohydrate
  • Evening meal: 40-50g carbohydrate
Getting breakfast right
  • Glucose levels tend to swing up much more after breakfast and so you will need to be much more careful with both the type and amount of carbohydrate at this meal.
  • Most women find 15-20g carbohydrate works well at this time of day.
  • Breakfast cereal (except jumbo porridge oats) will cause glucose levels to rise out of range.
Breakfast choices (this can be repeated at 90 - 120 minutes later)
  • 1 slice whole-wheat toast with a topping e.g. poached or scrambled eggs / mushrooms / tomato / cheese / ham / bacon / another cold meat / avocado.
  • Or 1 small pot yoghurt (less than 15g total carbohydrate) with 1 chopped fruit or cup of berries and optional topping of chopped nuts.
  • Or 25g jumbo porridge oats mixed raw with crème fraiche and 1 cup berries and optional topping of chopped nuts.
  • Or 40g jumbo porridge oats cooked with water and single cream added to taste, and can flavour with cinnamon, cocoa powder, or an artificial sweetener.
Being active immediately after eating
  • Getting up and being active for 15-20 minutes after eating can make your post-meal glucose level up to 2mmol/l lower and so can really help achieve the post meal glucose range.
  • This can be going for a walk or being active around the house or workplace.
  • Avoid being inactive immediately after eating.
  • Think how you can structure post meal activity into your daytime routine e.g. timing a meal before walking to work, nursery, or school, eating breakfast earlier to allow time for activity after, getting support from family so can be active after your evening meal.
Bulking up meals with more protein and vegetables / salad

Eating more protein foods such as lean meat, fish, chicken, cheese, eggs, tofu, Quorn, pulses as well as vegetables will fill you up more and reduce feelings of hunger which may occur because of eating smaller carbohydrate portions. These foods help limit the rise in glucose after meals and help to avoid post meal hypos.

Accurate carbohydrate counting

Accurate carbohydrate counting is particularly important to support time in the healthy pregnancy range. Small inaccuracies in counting can cause a significant difference in post meal glucose levels, for example being out by 10g carbohydrate can increase blood glucose readings by 2-3 mmol. Weighing food is the most accurate method of carb counting, but there are several useful resources to help with carbohydrate counting:

  • Carbs & Cals book or app (Chris Cheyette & Yello Balolia, Publisher - Chello)
  • DAFNE Carbohydrate Portion booklet
  • MyFitnessPal app
  • Food labels – use the ‘total carbohydrate’ amount when working out how much carbohydrate is in the food.
  • Restaurant web sites – nutritional information

Consider weighing frequent foods once and then using the same bowl/ cup etc – to keep the portion constant.

Some find simplifying their meals by keeping their carbohydrate foods separate, works well, for example by avoiding mixed meals such as risotto or pasta bakes and keeping to one carbohydrate choice at a time.

If you would like to refresh your carbohydrate counting skills, please try one of the online courses listed below:

Snack choices

Snacking between meals can be helpful to avoid post meal hypos, help manage hunger and optimise nutrition.

Making snack choices healthy, high in fibre and avoiding refined forms of carbohydrate helps to keep glucose levels stable between meals.

Snacks eaten for the following reasons will not need to be covered with insulin:

  • Snacks eaten within two hours of a meal to avoid post meal hypos.
  • Snacks to avoid hypos – when sensor reading below 6 mmol/l with arrows down (see sensor handout – avoiding hypos).
  • To cover significant activity.

It can feel tempting to choose sweeter, more refined, carbohydrates such as cake or biscuits especially if trying to avoid a hypo. However, these foods, even if covered with insulin, make it difficult to keep the next pre-meal glucose in range.

Try to carry healthy snacks with you when away from home in case you get hungry.

Healthier snacks containing 10-15g carbohydrate:

  • 1 fruit portion (a helpful measure is an amount that you can fit your hand around).
  • 2 whole-wheat crispbreads or oatcakes with low fat cream cheese.
  • A small yoghurt pot.
  • 1 slice of wholemeal bread with cheese/nut butter/egg/other non-carbohydrate choice.
  • 3-5 small squares 70% or above cocoa solids chocolate.

The following snacks contain minimal carbohydrate and can be eaten any time without needing insulin:

  • Avocado
  • Boiled egg
  • Cherry, salad and plum tomatoes
  • Cooked meats
  • Cubes of cheese (try with cocktail onion or gherkin) mini mozzarella
  • Vegetable pieces such as celery, carrots, cucumber eaten alone or with a dip such as houmous, cream cheese or salsa
  • Natural nuts or mixed seeds
  • Olives
  • Small corn on the cob
  • Sugar free jelly
  • Sun blushed or sun-dried tomatoes
  • Vegetable pieces such as celery, carrots, cucumber eaten alone or with a dip such as houmous, cream cheese or salsa
Avoid eating carbohydrate late in the evening
  • Overnight can be as much as a third of your day, so getting glucose levels as near normal pre-bed and overnight makes all the difference to achieving that 70% time in range.
  • Most report that their glucose levels are better when they eat their evening meal before 7.30pm. If they get hungry in the evening that’s when they reach for the carbohydrate free snacks.
Stay in touch
  • It can be challenging to keep up with the changes in insulin requirements over the course of your pregnancy.
  • Sharing your glucose data once a week can help with this.
  • Use the pregnancy email to stay in touch.
Insulin requirements towards the end of pregnancy
  • Many find their insulin requirements stabilise as they reach the end of their pregnancy.
  • This is partly due to insulin resistance starting to level out, but also because they find they cannot eat as much.
  • Please let us know if you start to have more hypos or are having to significantly reduce your insulin doses. However, a 10% reduction in insulin requirements is normal from around 36 weeks.
  • At 32-36 weeks we will discuss your insulin regimen for labour and after birth.
  • Insulin requirements return to pre-pregnancy levels almost immediately after birth. It is important to keep a record of your recommended postnatal insulin regimen, so you know what to change to.
A word on weight gain
  • The body becomes more efficient at extracting energy from food during pregnancy and most find they do not need to eat more than usual until the last three months of pregnancy.
  • Your appetite and rate of weight gain are good guides as to whether you are getting enough energy from your diet.
  • It is not helpful to gain too much weight as this increases insulin resistance making it more difficult to keep glucose in the healthy range for pregnancy.
  • Gaining more weight than is healthy can increase other risks as mentioned earlier such as high blood pressure, pre-eclampsia, more difficult birth, poor wound healing, and unhealthy weight gain in baby.

The table below (sourced from the US Institute of Medicine due to lack of UK data) gives a guide for healthy pregnancy weight gain based on your pre-pregnancy body mass index. (BMI).

*If your BMI is 35 or over, you and your healthcare team may aim for lower than 5kg weight gain to reduce adverse risks to you and your baby.
BMI at start of the pregnancy Guide to weight gain during pregnancy
BMI at start of the pregnancy Less than 18.5 Guide to weight gain during pregnancy 12.5-18kg
BMI at start of the pregnancy 18.5-24.9 Guide to weight gain during pregnancy 11.5-16kg
BMI at start of the pregnancy 25-29.9 Guide to weight gain during pregnancy 7-11.5kg
BMI at start of the pregnancy 30 and over* Guide to weight gain during pregnancy 5-9kg
Physical activity

You may need to make more adjustments to your insulin and/or carbohydrates to cover physical activity up to 16 weeks to avoid hypos (as you are more insulin sensitive). You may need to reduce insulin or eat extra carbohydrate for activity during the early stages of pregnancy. After 16 weeks as you become more insulin resistant you may need to gradually make less adjustments for activity. Use your glucose sensor to help guide you. As you become more insulin resistant, extra activity will become a useful tool to help you keep your glucose levels in range, especially after meals.

Hypoglycaemia (‘hypos’)
  • When working to maintain your glucose levels within the range for pregnancy it is likely you will experience more hypos than usual, especially in the first 16 weeks when you are more insulin sensitive.
  • ’Mild’ hypos, although not pleasant and inconvenient, are not considered harmful to you or your baby.
  • You may find your hypo warning signs change. They can become more subtle during pregnancy, making it important to monitor your glucose levels more frequently.
  • It is recommended that you set your alarms and alerts to help you avoid hypos.
  • You might want to consider sharing your sensor data to have others support you.

You are more at risk of having a severe hypo in the first 16 weeks of pregnancy so you will need to be more careful to avoid hypos.

If you lose your hypo awareness or have a severe hypo (where you need third party assistance to treat) it is important to let us know immediately.

You will hopefully find the information from your glucose sensor helpful to avoid many hypos – please see more information in the sensor leaflet.

Some things to keep in mind for hypos

  • Treat blood glucose levels below 3.5 mmol/l as a hypo regardless of whether you feel hypo or not.
  • Carry hypo treating foods (such as glucose tablets, jelly sweets, Lift – glucose juice) on your person when away from home; keep some in the car and by the bedside.
  • Check glucose levels before having a daytime nap, especially in the afternoon, to ensure you are at a safe level. This is often when glucose levels drop lower. If your sensor is showing glucose below 6mmol/l with arrows down have a carbohydrate snack and ensure your glucose is stable before you sleep.
  • Keep an ‘in date’ Glucagon injection kit at home (in the fridge). Glucagon is an emergency hypoglycaemia treatment to be used only if someone is unconscious or unable to eat or drink. This is available on prescription from your GP. It is important that someone in your household is trained to give Glucagon, we are happy to provide this training. Glucagon is a hormone that prompts the liver to release glucose and therefore can only be used once every 24 hours.

Hypo treatment: See flowchart below.

Sensor glucose is 5-10 minutes behind your blood glucose level.

  • Always use a finger stick blood glucose to confirm a hypo if you are not experiencing any symptoms.
  • It is recommended that you confirm your blood glucose level with a finger stick after treating a hypo since your sensor can still be showing a low glucose when your blood glucose is recovering and back in range. If you use the sensor glucose level, you are more likely to over treat your hypo resulting in a higher glucose level later. You can then find yourself on that glucose roller coaster.
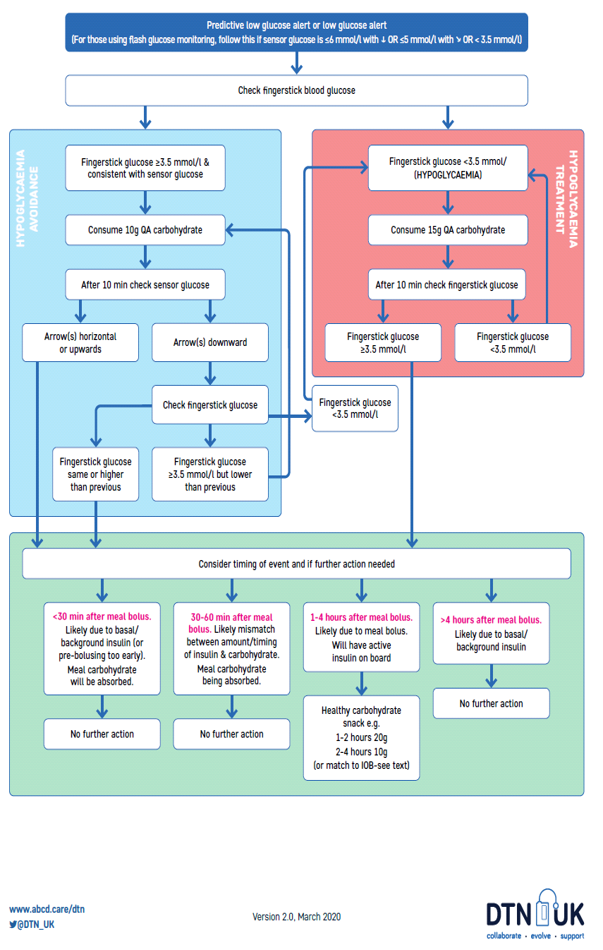
Flowchart showing guidance for managing low glucose alerts, including fingerstick glucose checks, treatment of hypoglycaemia with quick-acting carbohydrate, follow-up monitoring, and actions based on timing after meals and glucose results.
Carbohydrate options
Hypoglycaemia avoidance with about 5g carbohydrate Hypoglycaemia avoidance with about 10g carbohydrate Hypoglycaemia TREATMENT with 10g quick acting carbohydrate Hypoglycaemia TREATMENT with 15g quick acting carbohydrate
Fruit Hypoglycaemia avoidance with about 5g carbohydrate 1 tangerine/ satsuma/ plum/ 5 grapes/ 1 kiwi/ half very small banana Hypoglycaemia avoidance with about 10g carbohydrate 1 small apple/ pear/ orange/ peach/ 10 grapes/ 2 kiwi/ very small banana Hypoglycaemia TREATMENT with 10g quick acting carbohydrate Hypoglycaemia TREATMENT with 15g quick acting carbohydrate
Digestive biscuit Hypoglycaemia avoidance with about 5g carbohydrate ½ (half) Hypoglycaemia avoidance with about 10g carbohydrate 1 Hypoglycaemia TREATMENT with 10g quick acting carbohydrate Hypoglycaemia TREATMENT with 15g quick acting carbohydrate
Ryvitta Hypoglycaemia avoidance with about 5g carbohydrate ½ (half) Hypoglycaemia avoidance with about 10g carbohydrate 1 Hypoglycaemia TREATMENT with 10g quick acting carbohydrate Hypoglycaemia TREATMENT with 15g quick acting carbohydrate
Oatcake Hypoglycaemia avoidance with about 5g carbohydrate 1 Hypoglycaemia avoidance with about 10g carbohydrate 2 Hypoglycaemia TREATMENT with 10g quick acting carbohydrate Hypoglycaemia TREATMENT with 15g quick acting carbohydrate
Dark chocolate (70% cocoa) Hypoglycaemia avoidance with about 5g carbohydrate 15g total weight Hypoglycaemia avoidance with about 10g carbohydrate 30g total weight Hypoglycaemia TREATMENT with 10g quick acting carbohydrate Hypoglycaemia TREATMENT with 15g quick acting carbohydrate
Popcorn (salted or natural) Hypoglycaemia avoidance with about 5g carbohydrate 10g total weight Hypoglycaemia avoidance with about 10g carbohydrate 20g total weight Hypoglycaemia TREATMENT with 10g quick acting carbohydrate Hypoglycaemia TREATMENT with 15g quick acting carbohydrate
Smooth orange juice Hypoglycaemia avoidance with about 5g carbohydrate 50mls Hypoglycaemia avoidance with about 10g carbohydrate 100mls Hypoglycaemia TREATMENT with 10g quick acting carbohydrate 100mls Hypoglycaemia TREATMENT with 15g quick acting carbohydrate 150mls
Lift glucose tablets Hypoglycaemia avoidance with about 5g carbohydrate 1 Hypoglycaemia avoidance with about 10g carbohydrate 2 Hypoglycaemia TREATMENT with 10g quick acting carbohydrate 2 Hypoglycaemia TREATMENT with 15g quick acting carbohydrate 3
Lift Shot (previously Glucojuice) Hypoglycaemia avoidance with about 5g carbohydrate 1/3rd (one third) of bottle Hypoglycaemia avoidance with about 10g carbohydrate 2/3rd (two thirds) of bottle Hypoglycaemia TREATMENT with 10g quick acting carbohydrate 2/3rd (two thirds) of bottle Hypoglycaemia TREATMENT with 15g quick acting carbohydrate 1 bottle
Glucose tablets Hypoglycaemia avoidance with about 5g carbohydrate 2 Hypoglycaemia avoidance with about 10g carbohydrate 3 Hypoglycaemia TREATMENT with 10g quick acting carbohydrate 3 Hypoglycaemia TREATMENT with 15g quick acting carbohydrate 5
Jelly babies Hypoglycaemia avoidance with about 5g carbohydrate 1 Hypoglycaemia avoidance with about 10g carbohydrate 2 Hypoglycaemia TREATMENT with 10g quick acting carbohydrate 2 Hypoglycaemia TREATMENT with 15g quick acting carbohydrate 3
Nighttime hypos
  • Aim for glucose levels to be around 6.0-6.5mmol/l before bed (unless guided otherwise by your team).
  • If you see arrows down on your sensor work to stabilise them before going to sleep to avoid hypos in the night.
  • If you have been physically active towards the end of the day or had a hypo earlier in the day and your glucose is less than 6.5mmol/l before bed you should consider an insulin free snack of 10g total carbohydrate.
Ketones
  • Pregnant women are more likely to produce ketones, which can be part of the changes that normally occur in pregnancy.
  • Showing small amounts of ketones at times, especially if you have gone a long stretch without eating e.g. overnight, with glucoses in the normal range, is not a cause for concern.
  • Showing ketones regularly and losing weight can be a sign that you are not eating enough.

Test for ketones using a blood ketone meter if your glucose levels are running above 10mmol/l (on more than two consecutive occasions) or you are unwell.

In the same way high ketone levels are not good for you, they are not good for your baby.

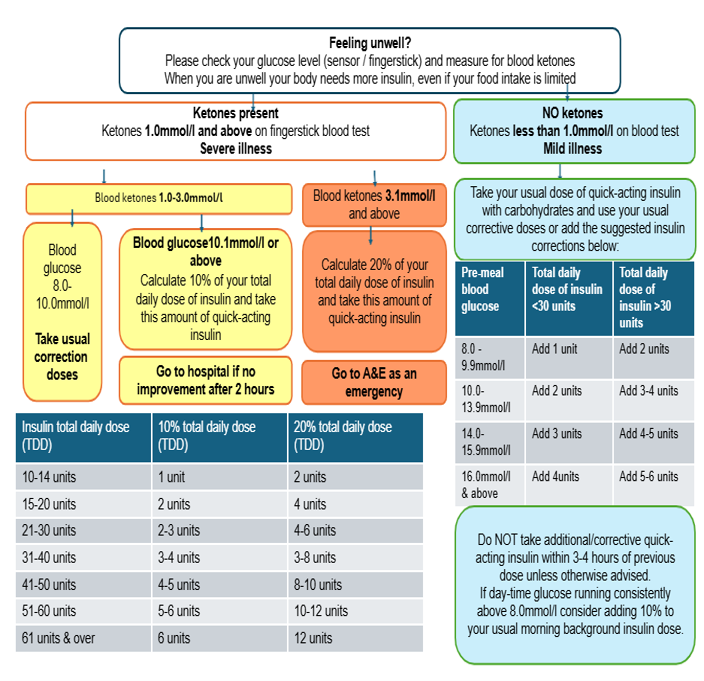
Sick Day Rules (SDR)

If feeling unwell or your glucose levels are running above 10mmol/l check for ketones (using a blood ketone meter) and start following the Sick Day Rules – see sheet at end of the document.

  • Check glucose and ketone levels more frequently – see sheet at end of the document.
  • Drink plenty of carbohydrate free fluids to avoid dehydration (100mls per hour or 2.5 litres per day).
  • If you can, continue to eat regularly.
  • If your appetite is poor try small amounts of carbohydrate regularly; 20g carbohydrate with insulin every 2-4 hours (yogurt, milk, soup, fruit juice, biscuits, toast, plain ice-cream, fruit).
Make emergency contact for the following reasons
  • Blood ketones 3.0mmol/l and above (go to hospital as an emergency)
  • Ketones remain at 1.1mmol/l after two hours (be prepared to go to hospital as an emergency).
  • Glucose running above 10mmol/l for more than six hours.
  • You continue to vomit or are unable to keep fluids down.
  • Having problematic hypos.
Nausea

Nausea or pregnancy sickness can be a problem in pregnancy and can affect you at any time of the day. Please speak to your GP if you need to consider medication to help with your symptoms.

The following suggestions may help but please mention this to us at your next appointment.

  • You may struggle to follow the dietary guidelines for pregnancy whilst struggling with nausea. Make a list of foods you can manage and bring to clinic so we can discuss how best to include these and help keep your blood glucose readings in range.
  • Avoid going long stretches of time without food.
  • Eat carbohydrate foods regularly throughout the day. Dry carbohydrate foods such as plain digestive biscuits and crackers like oatcakes or Ryvita may ease the nausea.
  • Try drinking fluids before or after meals and snacks, rather than with them.
  • Some people find ginger teas or peppermint teas can help with nausea.
  • Avoid strong food smells.
  • If you are unable to eat or drink without vomiting, please call your diabetes educator, GP, or Clinic 23 (see contact numbers on page 18) for help.
  • If you are concerned about giving insulin when you may vomit, you can take 1/2 - 1/3 (a half or a third) of your mealtime insulin before eating and the rest up to an hour after eating when you are sure you are not going to vomit.
  • If you are experiencing frequent hypos (blood glucose levels below 4.0mmol/l) due to vomiting, please contact a member of the diabetes team for advice.
Reasons to contact the Rosie hospital
  • Vomiting continuously, it may be necessary to admit you to prevent dehydration.
  • Pain or feeling unwell for an unknown reason.
  • Bleeding or water loss from the vagina.
  • Baby movements; changed, reduced or stopped.

Less than 13 weeks contact the early pregnancy unit: telephone: 01223 217636

More than 13 weeks contact clinic 23 (assessment unit): telephone: 01223 217217

Eyes
  • The national eye screening programme will be informed of your pregnancy, and you should be contacted to be screened in the first trimester. Please contact us if you have not received an appointment. Any eye changes present may worsen during pregnancy. If you are concerned about this, please ask at your next appointment.
  • If you attend the eye clinic you should inform them of your pregnancy as you may need to be seen more frequently.
  • You should seek an urgent assessment if you experience blurred vision, flashes of light, new floaters or a change in vision. This can be a sign of changes to your eyes or indicate pre-eclampsia (high blood pressure) is developing later in pregnancy.
Blood pressure

This will be measured at every appointment to screen for pre-eclampsia (high blood pressure in pregnancy) and to monitor pre-existing blood pressure problems.

National pregnancy in diabetes audit
  • This is a programme run by NHS England Digital.
  • This audit collects anonymous data about your pregnancy and baby to better inform how to deliver the best care for all women with diabetes in pregnancy.
Obstetric care during pregnancy

Pregnancy in women with diabetes is classed as ‘High Risk’.

Your pregnancy will be closely monitored by the obstetric team using scans and foetal monitoring for the growth and well-being of your baby. NHS Choices website has a link for specific advice about pregnancy.

It is important to continue to see your community midwife throughout your pregnancy for routine antenatal care.

Early pregnancy - up to 12 weeks

You will need to be seen by your community midwife early in your pregnancy for your “booking visit”. You will also need a notification of pregnancy, please see the Rosie hospital website for details of how to complete this.

Scans offered:

  • 7-9 weeks - early pregnancy scan.
  • 11-13 weeks - dating scan with option for nuchal screen.

Antenatal Clinic (ANC) booking visit with the obstetric team, which is requested for a time after your dating scan.

It is recommended that along with your booking bloods that you would have blood tests to check your HbA1c, kidney function and thyroid function.

Aspirin: for most women we will recommend taking 150mg Aspirin daily from 12 weeks to reduce the risk of pre-eclampsia.

You will be offered appointments to see the diabetes team every 1-3 weeks depending on how much support is needed to optimise glucose levels. At these appointments we will request a urine sample, and we will order blood tests as necessary.

Mid pregnancy - 13-26 weeks

Scans offered:

  • 20 weeks in the Foetal Medicine department (Clinic 22) to review the development and well-being of your baby.

Please remember to book your antenatal classes if this is your first pregnancy.

At 24 weeks gestation we ask you to have a HbA1c which we are aiming to be as close as possible to 42mmol/. This has been shown to reduce pregnancy risks.

Late pregnancy - 27-39 weeks

Scans (growth) offered to assess the growth of your baby, the fluid around your baby (liquor volume) and blood flow through the cord:

  • 28 weeks scan and routine bloods plus diabetes bloods; HbA1c, kidney function and thyroid if needed
  • 32 weeks scan
    • 34 weeks scan if HbA1c above 48mmol/l or some other clinical indicator
  • 36 weeks scan

You will be offered appointments with the diabetes and / or obstetric teams after each scan. Your diabetes medication needs for the birth and after the birth of your baby will be discussed with you around 32 to 36 weeks and will be documented in your notes.

Towards the end of your pregnancy

Research shows that the placenta can age a little earlier in pregnancy when you have diabetes.

Please look out for:

  • Your baby’s movements; changed, reduced or stopped
  • Significant reduction in insulin requirements
  • Increased frequency of hypos

Please contact the Maternity Assessment line 01223 217217 (open 24 hours a day) the same day you notice the change.

Birth

You will have the opportunity to discuss your birth plan with the obstetric team at around 32 to 34 weeks. The birth will be planned to take place from the 38th week of your pregnancy (NICE guidance advises that your baby should be born before your due date).

Hospital admission

When you come into hospital it may be useful to have a checklist for things you will need for your diabetes care.

Remember to bring your:

  • Blood glucose meter and plenty of test strips and lancets
  • Spare sensor
  • Spare batteries
  • Insulin (quick acting and background) plus pen devices
  • Snack foods that have worked well in pregnancy
  • Hypo treating foods or drinks
  • Sugar free drinks

It is recommended that your baby is born on the Delivery Unit where the full maternity care team (including obstetricians, midwives, and anaesthetists) can provide the recommended monitoring and support for you and your baby.

Your insulin requirements during labour are likely to remain the same as they are at the end of your pregnancy.

You are aiming to keep your blood glucose levels between 5.0 and 8.0mmol/l throughout labour to reduce the chance of low glucose levels (neonatal hypoglycaemia) after birth.

If for any reason you do not feel able to manage your own glucose levels during labour or your glucose levels are running outside the range 5.0 to 8.0mmol/l you can be changed to a ‘variable rate intravenous insulin infusion’ (insulin through a vein) to maintain optimal glucose levels.

Immediately after the birth of your baby:

Your insulin requirements will return to pre-pregnancy levels within 24-48 hours after birth, so remember to change to your post-natal insulin regimen immediately after the birth of your baby.

  • You should also change your sensor settings to ‘postnatal’.
  • Do not give any quick acting insulin with your first food after birth.
Supporting your baby after birth
  • It is helpful to offer your baby a feed within an hour of being born as this can reduce the risk of them having a lower blood glucose.
  • Keeping ‘skin to skin’ contact with your baby in the first few hours, or as long as you want will help to encourage regular feeding and keep your baby warm and calm which has been shown to help keep their glucose in a healthy range.
  • You can learn to hand express colostrum from 36 weeks and store it in the freezer so that if your baby has a low blood glucose level or needs extra feeds you have your own milk to give them. We can demonstrate this to you at your 36 weeks clinic visit.
  • Your baby will have regular blood glucose monitoring during the first 24 hours after birth. Some babies require support to help stabilise their blood glucose levels after birth.
Feeding your baby

Your breastmilk is made exactly right for your baby, and it constantly changes to meet their needs as they grow.

Breastmilk also contains helpful things that no other milk can, including:

  • Special factors that promote growth.
  • Antibodies that provide protection for your baby against infection.

Breastfed babies are less likely to develop; type 1 diabetes, allergies, become obese (with associated risks for heart disease and type 2 diabetes).

If you choose to feed your baby formula milk it is helpful to feed them regularly, responding to their feeding cues, to help support their glucose levels in a healthy range. Keeping your baby close with ‘skin to skin’ time will help with this. If you would like to give your baby colostrum, or to give the first feed as a breastfeed, this has many health benefits. Please speak to a midwife in the diabetes team if you are interested in this.

  • Insulin requirements are lower when breastfeeding, this will have been considered when working out your postnatal insulin requirements.
  • You will need to eat extra carbohydrate to meet the demands of milk production, usually about an extra 30-60g carbohydrate (an extra 200-500 kcals) each day. Most women find their appetite during breastfeeding meets their increased needs, but if you are unsure of your diet, please discuss this with your diabetes dietitian.
  • Breastfeeding stimulates milk production, which in turn causes glucose levels to fall towards the end of the feed or shortly after, increasing the risk of a hypo.
  • Check your sensor glucose frequently, before and after the feed, to help learn how breastfeeding affects your glucose levels and best ways to manage.
  • You can reduce the risk of having a hypo by eating a small insulin free carbohydrate snack (10-15g) with each feed. You are likely to find, as breastfeeding becomes established, that this is needed less.

Checking your blood glucose before and after feeds will help you get this right.

  • Keep hypo-treating foods by the bed or chair where you plan to feed your baby, so everything is to hand in case your glucose does drop low.
  • If you choose to bottle feed it is still important to keep your baby close and have ‘skin to skin’ time, as this will help with bonding and is calming for both of you.
After the birth and follow up:
  • It can take some time for your glucose levels to settle down after your baby is born.
  • Life with a new baby is unpredictable as your sleep patterns change as you meet your baby’s needs for responsive feeding.
  • During the early months aim for your glucose to run between 6-10mmol/l over the day, and do not worry if you see the occasional rise to 12-15mmol/l after meals.
  • Continue to use your glucose sensor to check your glucose regularly as you adjust to life with a new baby, especially if you are breastfeeding.
  • As you become more settled in your new routines you can nudge your targets down to 4-10mmol.
  • You will be offered a follow up appointment in the post-natal diabetes clinic 6-8 weeks after the birth of your baby, if you do not receive this appointment by 5-6 weeks after your baby is born, please get in touch.
  • We encourage you to keep in contact with the diabetes team for support during the early days and weeks of new motherhood.

You should see your GP for your routine postnatal mother and baby checks. Please ask your GP to request a routine thyroid function blood test whether or not you have a history of thyroid dysfunction. Please ensure you take the opportunity to discuss contraception at this visit. Breastfeeding alone is not a reliable form of contraception. We can offer certain types of LARC – long-acting reversible contraception – prior to your discharge from the ward. These are safe with breastfeeding. Please ask.

For more information, please take a look here:

Or

Useful contacts

Email: Diabetes and pregnancy educators

EMERGENCY diabetes out of hours on-call service: 01223 960993

Monday to Friday 4pm-11pm & 6am-9am, weekends and bank holidays 6am-11pm

Diabetes specialist midwives
(08:00 to 18:00 Mon-Fri)
01223 217657 (answer machine)
Diabetes specialist nurses
(09:00 to 16:00 Mon-Fri)
01223 348780 (answer machine)
Diabetes specialist dietitians
(09:00 to 17:00 Mon-Fri)
01223 349471 (answer machine)
01223 348905 (answer machine)
Appointments
(09:00 to 17:00 Mon-Fri)
01223 217664
01223 257185
Scan department
(08:30 to 16:00 Mon-Fri)
01223 217621
Clinic 24
(for pregnancies under 13 weeks gestation)
01223 217636
Delivery unit 01223 217217
Maternal assessment unit
(Clinic 23)
01223 217 217
SDR guidance
Sick Day Rules (SDR) Guidance

Go to hospital as an emergency if any of these apply, please continue to follow all other recommendations until you are informed otherwise:

  • Blood ketones 3.1mmol/l and above
  • Blood ketones not improving and above 1.1mmol/l after 2 hours
  • Blood ketones still 1.1mmol/l or above after 6 hours
  • You are having hypos
  • You continue to vomit or are unable to keep fluids down

  • Every 2 hours - measure your blood glucose and blook ketone levels, if ketones remain 1.0mmol/l then take 10% TDD quick-acting insulin every 2 hours until ketones less than 1.0mmol/l.
  • Keep hydrated - sip sugar free liquids (e.g. water, diet drinks or sugar free cordials), at least 100ml every hour.
  • Try to maintain some energy intake - eat as usual, if you are able and continue to give your usual bolus of insulin.
  • If you are struggling to eat, try with carbohydrate snacks (e.g. yoghurts, fruit, digestives, crisps) or drink milk or an alternative drink containing sugar.

We are smoke-free

Smoking is not allowed anywhere on the hospital campus. For advice and support in quitting, contact your GP or the free NHS stop smoking helpline on 0800 169 0 169.

Other formats

Help accessing this information in other formats is available. To find out more about the services we provide, please visit our patient information help page (see link below) or telephone 01223 256998. www.cuh.nhs.uk/contact-us/accessible-information/

Contact us

Cambridge University Hospitals
NHS Foundation Trust
Hills Road, Cambridge
CB2 0QQ

Telephone +44 (0)1223 245151
https://www.cuh.nhs.uk/contact-us/contact-enquiries/